

Your Journey to Smoother Skin Starts Here
The need isn't for more treatment menus. What's needed is clarity.
By the time someone books an acne scar consultation, they've usually already tried the common route. Strong skincare. Home devices. Peels marketed as resurfacing. Advice from social media that treats every post-acne mark as if it behaves the same way. That's how people lose time, and sometimes worsen irritation without changing the actual scar structure.
True acne scars are structural. They sit below the skin's surface, involve collagen loss or abnormal collagen repair, and need a treatment plan that matches that anatomy. That's why effective acne scar removal is rarely a single-session answer and almost never the same for every face.
Three factors shape the right plan more than anything else:
- Scar shape and depth: Rolling scars, boxcar scars, ice pick scars, and raised scars respond differently.
- Skin tone and healing response: Pigment risk matters, especially if you're prone to post-inflammatory hyperpigmentation.
- Lifestyle and downtime tolerance: Some people can manage visible recovery. Others need approaches with less surface disruption.
Practical rule: Don't choose a treatment because it's popular. Choose it because it solves the physical reason your scar exists.
Acne scarring is often mixed. For example, someone may have broad rolling scars on the cheeks, a few deep boxcar scars, and flat pigmentation from previous inflammation. If you treat only the colour, the texture remains. If you resurface without releasing tethering, the skin may still look uneven.
That's why good practitioners think in layers. They ask what needs releasing, what needs remodelling, what needs lifting, and what needs leaving alone. Once you approach scarring that way, the range of treatments becomes much less confusing.
How I Picked These Treatments
Before comparing devices, it helps to know what this guide is basing its recommendations on. Four criteria shaped every judgement below:
- Scar-type evidence: does the treatment have published data for the specific scar pattern it's being recommended for, not just acne scarring in general?
- Skin-tone safety: how does the option perform in Fitzpatrick IV to VI skin, where post-inflammatory hyperpigmentation is the main avoided complication?
- Downtime and recovery reality: can a working adult realistically complete the course, including visible healing days?
- Strength of the underlying evidence: randomised trials and systematic reviews rank above clinic marketing and before-and-after lighting.
The scarring problem itself is well documented. Acne affects up to 80% of people aged 11–30, and in a large US dermatology-practice study of 1,956 participants, 43% were identified as having acne scars — clinically significant scarring is generally reported in roughly half of patients who develop acne, according to a dermatology review on acne scarring. That scale is why treatment choices deserve more rigour than a trending hashtag. In practice, many patients spend years on the wrong category of treatment because nobody matched the device to their scar shape.
Where the evidence is mixed, as it is for chemical peels in scar revision, I say so rather than presenting every option as equally proven.
First Understand Your Acne Scars
Before choosing any device or procedure, identify whether you're dealing with true scars, post-acne marks, or both. Patients often call everything a scar, but from a treatment point of view, the difference is essential. For a broader overview of how acne scars form and behave, Neutralyze's guide is a useful plain-English companion to this section.
Scars and marks are not the same thing
If the skin is flat and only the colour has changed, that's usually a mark rather than a textural scar. Brown marks are commonly post-inflammatory hyperpigmentation. Red or pink post-acne marks can also linger long after the breakout has settled. These can improve with time and targeted skincare, whereas true scarring changes the skin's surface contour.
A simple check helps. Look at the area in side lighting and gently stretch the skin. If the indentation or raised area remains visible, that usually points to structural change rather than pigment alone.
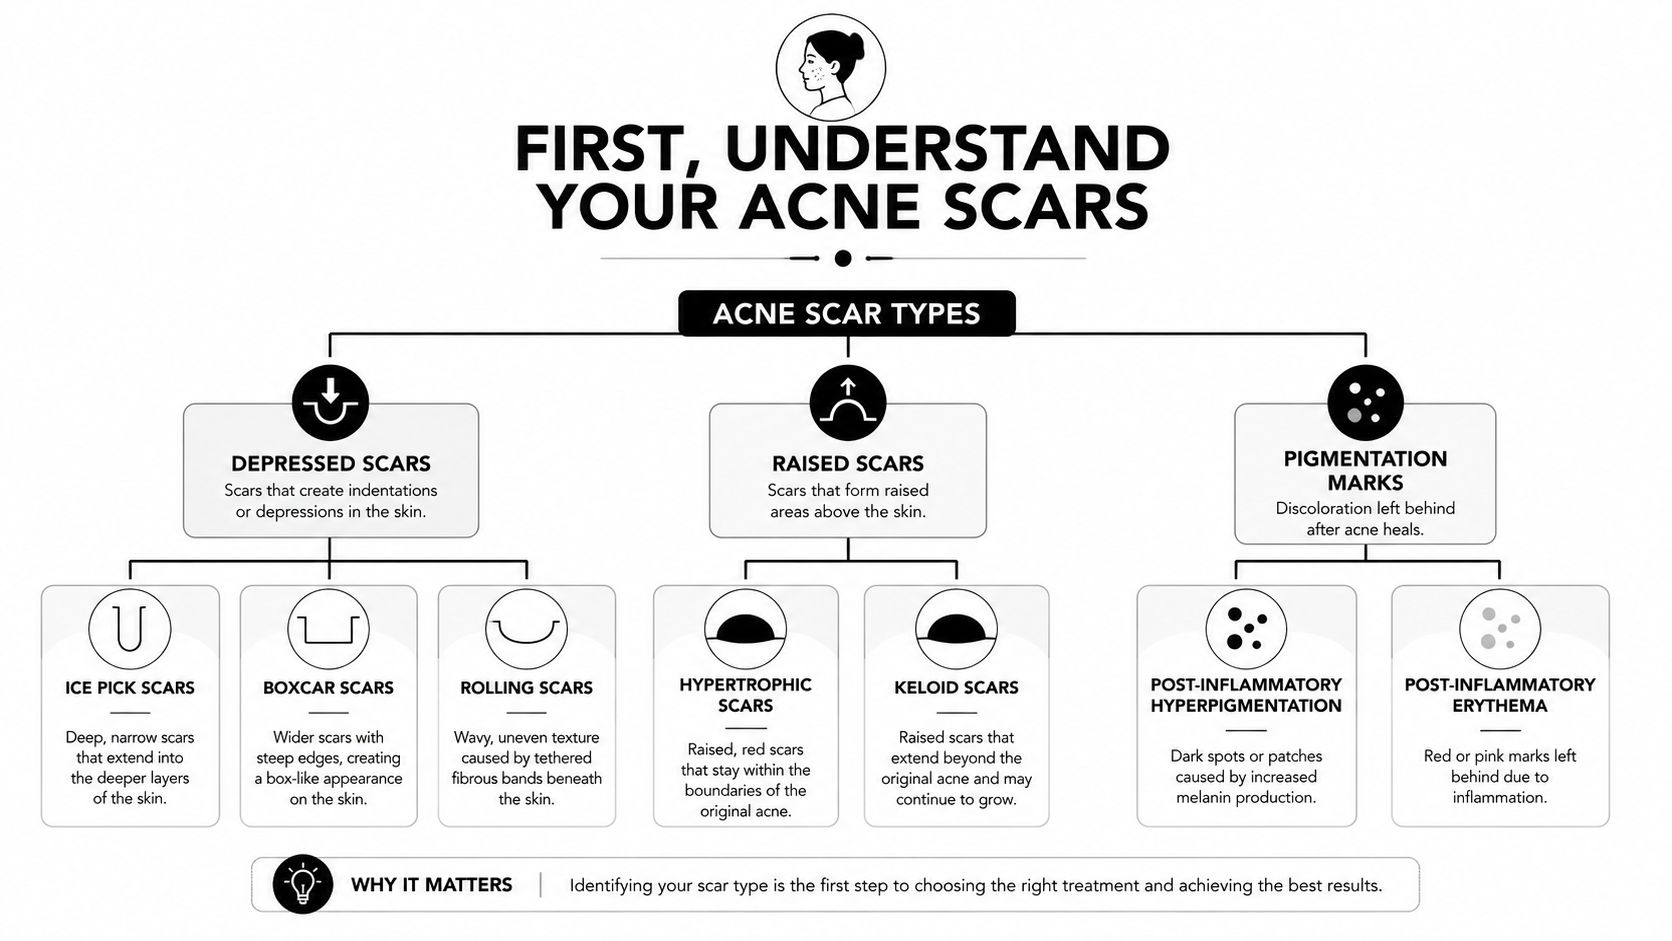
The main scar types to recognise
Most acne scars fall into two broad groups. Atrophic scars are depressed or indented. Hypertrophic or keloid scars are raised.
Here's what that usually looks like in practice:
- Ice pick scars: These are narrow and deep. They look like tiny punctures that drop sharply into the skin. They're among the hardest scars to improve with broad resurfacing alone because the opening is small but the depth is significant.
- Boxcar scars: These are wider than ice pick scars and have clearer edges. They can be shallow or deep. When they're deeper and sharply defined, they often need stronger structural treatment.
- Rolling scars: These create soft undulations or wave-like unevenness. They're often tethered below the surface by fibrous bands, which is why resurfacing on its own may not be enough.
- Hypertrophic scars: These are raised but remain within the original breakout area.
- Keloid scars: These extend beyond the original site and reflect an overactive healing response.
A mixed pattern is common. Someone may not have “one type” of acne scar at all. That's where self-diagnosis starts to break down and professional assessment becomes useful.
If your scars look shallow from the front but pronounced in angled light, rolling or tethered scarring is often involved.
It's also worth noting what won't qualify as scar removal. Topical brightening products can improve tone. Exfoliation can refine the surface. Neither can reliably rebuild a deep collagen deficit on its own.
The more accurately you recognise your scar pattern, the easier it becomes to understand why one person is advised to have fractional CO2, another RF microneedling, and another a staged plan with subcision before any resurfacing at all.
A Detailed Comparison of Acne Scar Treatments
A patient often arrives saying the same thing. “I have tried microneedling, peels, and skincare, but the scars still show in certain light.” In clinic, the reason is usually straightforward. The treatment addressed surface texture, but the scar needed release, deeper remodelling, or a staged plan that matched both scar type and skin tone.
Different treatments do different jobs. Some smooth the surface. Some stimulate collagen at depth. Some release fibrous tethering. Some add temporary lift where volume loss is the main issue. Selecting the most appropriate acne scar treatment UK clinics offer is rarely about one device used repeatedly without a clear reason. It is usually a customized combination chosen with restraint, especially in patients with darker skin where overtreatment can leave pigment changes that are harder to correct than the scar itself.
Acne Scar Treatment Comparison Matrix
| Treatment | Best For (Scar Type) | Average Downtime | Expected Sessions | Cost per Session (£) |
|---|---|---|---|---|
| Fractional CO2 laser | Boxcar scars, deeper atrophic scars, significant textural resurfacing | 5 to 10 days | 1 to 3 | £600 to £1,500 |
| Picosecond laser | Mild to moderate atrophic scars, patients wanting less downtime than ablative resurfacing | 2 to 5 days | 3 to 6 | £350 to £900 |
| Microneedling | Mild textural scarring, early atrophic scars, general collagen support | 1 to 3 days | 3 to 6 | £180 to £350 |
| RF microneedling | Rolling scars, mixed atrophic scars, deeper remodelling with lower surface injury | 2 to 5 days | 3 to 4 | £300 to £700 |
| Chemical peels | Surface irregularity, post-acne pigmentation, mild textural refinement | 1 to 7 days, depending on peel depth | 3 to 6 | £120 to £300 |
| Subcision | Rolling scars, tethered depressions | 3 to 7 days, sometimes with bruising | 1 to 3 | £350 to £800 |
| Dermal fillers | Selected rolling or boxcar scars needing lift | 1 to 3 days | 1, then maintenance if needed | £300 to £900 |
These are realistic private clinic ranges in the UK market, not fixed quotes. Final cost depends on treatment area, scar density, practitioner experience, device used, and whether treatments are combined in the same plan. At our own clinic, CO2 laser scar removal with the 3D Vjuve starts from £250 per session as an entry price for a specific offering — it's one of the few treatments we offer with genuine downtime.
For a quick visual overview of treatment options and skin remodelling, this walkthrough is useful:
Acne scar treatment video overview
Laser resurfacing and collagen remodelling
Fractional CO2 laser remains one of the strongest options for deeper atrophic acne scarring. It works by creating controlled columns in the skin that trigger significant collagen remodelling while also resurfacing the upper layers. A review covering atrophic acne scar treatments reported meaningful improvement with fractional CO2 across multiple studies, particularly in boxcar and broader atrophic scars.
The trade-off is downtime, aftercare, and pigment risk. In lighter skin tones with the right indication, CO2 can be excellent. In darker skin, or in anyone prone to post-inflammatory hyperpigmentation, I would only consider it after careful assessment and preparation. An aggressive approach is not automatically the right one.
Picosecond laser has a different role. It can improve atrophic scars with less surface disruption than ablative laser, which makes it attractive for patients who want a shorter recovery period or need a more cautious approach. In peer-reviewed clinical data on picosecond laser treatment, researchers reported significant scar improvement with a favourable safety profile and no severe adverse events in the reviewed studies.
That safety profile matters in practice. Picosecond technology is often more realistic for patients who cannot accommodate a week of visible recovery, and for some patients with medium to darker skin tones who need lower epidermal injury. It is still not the answer for every deep scar. Very narrow or heavily tethered scars usually need something more targeted.
Deeper resurfacing only helps when the scar pattern actually calls for it.
Microneedling and RF microneedling
Standard microneedling is often oversold online. It has value, but its role is narrower than many patients expect. It can improve mild textural change, support collagen production, and suit patients who want a lower-cost starting point with minimal downtime. It is less convincing for deep boxcar scars, ice pick scars, or scars that are visibly tethered.
RF microneedling reaches deeper and adds thermal energy in the dermis. That gives it a different profile from standard needling. It is often useful for rolling scars and mixed atrophic scarring, especially when the aim is to remodel deeper tissue while keeping the surface barrier more intact than an ablative laser would.
In a split-face comparative study of radiofrequency microneedling and fractional CO2 for acne scars, both treatments improved atrophic scars, while radiofrequency microneedling showed a more favourable side-effect profile. That is one reason many practitioners use it in skin types where pigment disruption is a bigger concern.
Results are gradual. That can frustrate patients who expect a dramatic change after one session. In reality, RF microneedling is often part of a course, and the best outcomes come when the scar type is suitable and tethering has not been overlooked.
The evidence on improvement is more consistent than patients assume, but the degree matters. A 2017 systematic review found microneedling studies reported visible improvement in every treated patient, ranging from 31% to 62%; chemical approaches varied far more, with 20% glycolic acid producing no improvement at all in a quarter of participants in one study. Asking “which device” matters less than asking “what magnitude of improvement does the evidence show?”
Subcision, fillers and surface-focused options
Subcision is one of the most important treatments for rolling scars, yet it is often left out of generic acne scar guides. It addresses the mechanical problem beneath the scar by releasing the fibrous bands that pull the skin downward. If that tethering remains in place, resurfacing alone may soften the area but leave the shadowing behind.
This is a common reason patients feel disappointed after laser elsewhere. The device may have been used correctly, but the treatment plan did not match the scar architecture.
Dermal fillers can help selected depressed scars by lifting the base and reducing visible depth. Their effect is immediate, which patients often like, but they do not replace proper scar revision in every case. Fillers are best used selectively, either as a finishing step or where volume loss is a major part of the problem. Maintenance is also part of the conversation because most filler outcomes are not permanent.
Chemical peels are useful for the skin around the scar as much as the scar itself. They can improve dullness, post-acne marks, uneven tone, and very mild textural irregularity. They are rarely the main treatment for established deep acne scarring. In darker skin tones, peel choice and strength need particular care because an aggressive peel can trigger pigmentation that keeps the skin looking uneven even if the texture improves.
A practical way to compare these categories is by the job they perform:
- Resurface: Fractional CO2 laser, selected chemical peels, picosecond laser in appropriate cases
- Remodel collagen: Microneedling, RF microneedling, laser-based collagen stimulation
- Release tethering: Subcision
- Lift selected depressions: Dermal fillers
The best plans are usually layered, not excessive. One patient may need subcision first, then RF microneedling. Another may suit fractional CO2 after careful pigment-risk assessment. Another may do better with a slower, safer course because skin tone and healing behaviour matter as much as scar depth. That is the part many treatment lists miss, and it is exactly why a good consultation should sort scars by structure, not by trend.
The direction of recent research supports layering. A 2025 network meta-analysis of 68 randomised controlled trials involving 4,480 patients found laser combined with PRP ranked strongest for reducing ECCA scar scores, with a SUCRA value of 98.4%, while laser combined with filler scored highest on the Global Assessment Scale. ECCA stands for Échelle d'Évaluation Clinique des Cicatrices d'Acné, a clinical grading scale used to measure acne scar severity. SUCRA, or Surface Under the Cumulative Ranking curve, is a statistical score from 0 to 100 that indicates how likely a treatment is to be the best among those compared; a higher number means a stronger ranking. Using multiple modalities together is now supported by strong evidence rather than being an optional add-on.
How to Choose the Right Treatment for Your Scars
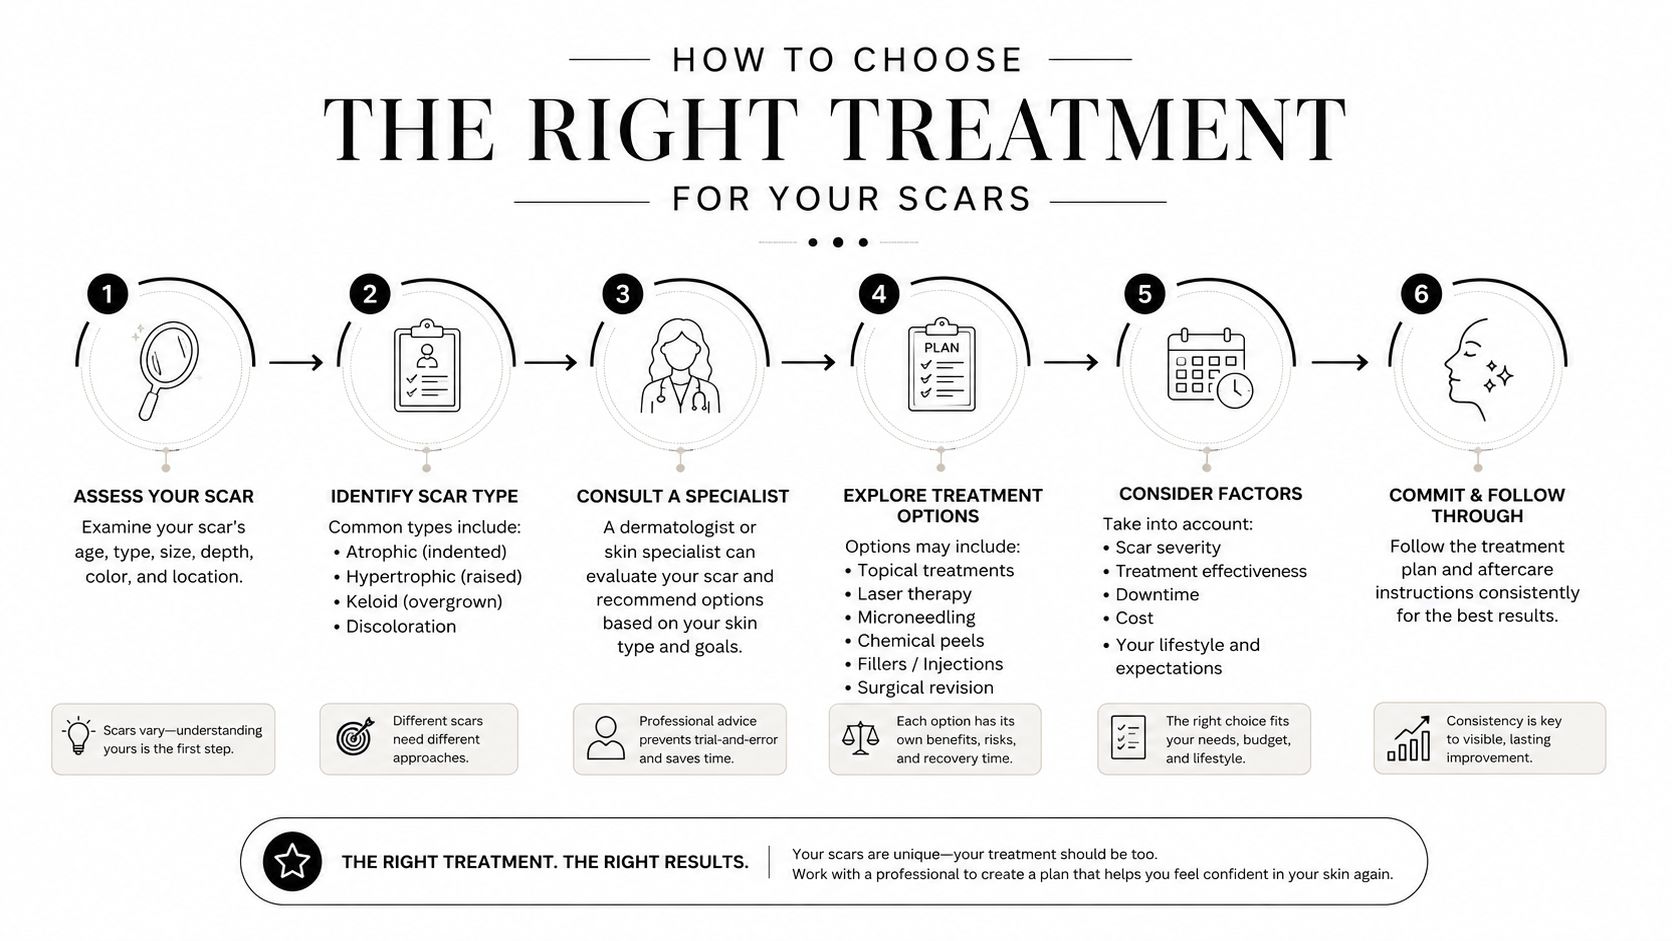
The right plan should follow the scar, not the trend. Device-led marketing often encourages people to think in treatment names. Clinical logic works the other way round. Start with the physical problem, then choose the tool.
The strategy for ice pick and narrow deep scars
Ice pick scars are notoriously stubborn because they're deep and narrow. Broad collagen stimulation may soften the surrounding skin, but it often won't fully change the look of a sharply punctate scar.
For this pattern, the most sensible plan is usually a targeted approach first, followed by overall skin remodelling if needed. If someone tries to treat a face full of ice pick scars with only gentle microneedling, they often spend time and money without getting the change they hoped for.
Decision point: If the scar is tiny at the opening but deep in profile, choose precision before general resurfacing.
The strategy for boxcar and rolling scars
Boxcar scars and rolling scars are where many modern treatments perform well, but only when the distinction is made properly.
Deep boxcar scars often respond better to stronger resurfacing or layered correction because the edges are defined and the tissue loss is more obvious. Fractional CO2 can be a strong option for this pattern when the patient is suitable and accepts the trade-off of more downtime.
Rolling scars need a different mindset. If the skin is being pulled downward by fibrous bands, subcision often makes more sense as the first move. Once the tethering is released, RF microneedling or laser treatment can improve the surrounding texture and collagen quality more effectively.
That sequencing matters. If you reverse it, the result can be modest because the scar's main mechanical cause remains in place.
Here's a practical consideration:
- Deep boxcar scars: Strong resurfacing, sometimes combined approaches
- Rolling scars with movement or tethering: Release first, then remodel
- Mixed cheek scarring: Combination plans usually outperform single-modality repetition
Raised scars and mixed-pattern scarring
Raised scars sit in a completely different category from depressed scars. A lifting treatment won't flatten a raised scar, and resurfacing a clearly keloid-prone area without care can create avoidable problems.
Mixed-pattern scarring is where customized treatment matters most. It's common to see:
- rolling scars across the cheeks
- a few boxcar scars near the temples
- lingering pigmentation around the jawline
- isolated raised scars on the body or lower face
That person doesn't need a single universal solution. They need the best combination for each scar behaviour.
A good consultation usually narrows decisions using four questions:
- Which scars are structural?
- Which are tethered?
- Which treatments carry unnecessary pigment risk for this skin tone?
- What result matters most to the patient, smoother texture, softer depth, or more even skin overall?
When those answers are clear, treatment planning becomes much more rational and far less frustrating.
A Crucial Guide for Different Skin Tones
One of the biggest gaps in acne scar advice is the assumption that every resurfacing option carries the same risk across every skin tone. It doesn't. That matters most for patients with medium to deep skin tones, especially Fitzpatrick IV to VI.
Why darker skin needs a different risk discussion
Darker skin contains more active melanin, which means inflammation can trigger longer-lasting pigment change. That doesn't mean effective acne scars treatment is off limits. It means the treatment choice, settings, prep, and aftercare need more care.
The Mayo Clinic guidance on acne scars explicitly warns that laser resurfacing carries increased side effect risks for people with darker skin, and identifies RF devices and non-ablative lasers as safer evidence-based alternatives that can tighten effectively with minimal surface damage and lower risk of post-inflammatory hyperpigmentation.
UK clinical guidance points the same way: when selecting laser parameters in darker skin, practitioners are advised to use conservative settings, longer intervals between sessions and test patches. Test patches are frequently overlooked, yet they prevent many complications.
Understanding this nuance is essential. Many generic treatment pages present laser as if it's automatically the premium option. In reality, for some patients, the premium choice is the one that reduces risk while still delivering meaningful improvement.
Safer treatment logic for Fitzpatrick IV to VI
For darker skin, the question shouldn't be “What is the strongest treatment available?” It should be “What gives visible improvement without provoking unnecessary inflammation?”
That often shifts the decision-making toward:
- RF microneedling: Useful because it targets deeper tissue remodelling with less surface trauma.
- Non-ablative laser options: Better suited when a patient needs collagen stimulation but has a higher pigment risk.
- Conservative resurfacing plans: Sometimes the right answer is lower settings, longer spacing, and staged improvement rather than a more aggressive single procedure.
Skin of colour doesn't need weaker treatment. It needs more precise treatment.
A practitioner should also ask about any history of post-inflammatory hyperpigmentation, delayed pigment settling, or keloid tendency. Those details often change the recommendation more than the scar photo itself.
Experience matters. A good plan for darker skin isn't about avoiding results. It's about choosing a route that respects how that skin heals.
Realistic Results Timelines and What to Expect
Many patients arrive with the same question in different words. Can acne scars be fully removed. In most cases, the honest answer is no. But that doesn't mean treatment isn't worth doing.
Why 100 percent removal isn't the right goal
Complete eradication is usually the wrong benchmark because acne scars are structural changes in the skin, not surface debris to be polished away. The more useful goal is visible softening, shallower depth, smoother transitions, and skin that stops drawing your attention every time you catch your reflection.
According to guidance on realistic acne scar outcomes from The Independent Pharmacy, complete 100% removal is medically unattainable for most scar types, but severe scars can see a 50–70% reduction with ablative lasers. That's a realistic result, and for many people it meaningfully changes their experience.

What a normal treatment journey feels like
Improvement usually arrives in layers.
Early on, patients may notice the skin looks brighter, more polished, or slightly firmer. Deeper scar change tends to follow more slowly because collagen remodelling takes time. That delay is one reason people underestimate progress mid-course. They compare one week to the next instead of comparing month one to month four.
A realistic treatment journey often includes:
- An assessment phase: Confirm scar type, skin tone risks, and whether active acne needs control first.
- A treatment phase: This may involve a course rather than one session, especially for collagen-stimulating procedures.
- A remodelling phase: Skin continues changing after the visible redness or downtime is over.
- A refinement phase: Some patients then add another modality to target what remains most noticeable.
Good acne scar work is cumulative. The skin often looks better because several small structural gains add up, not because one treatment erased everything.
The biggest disappointment usually comes from expecting one intervention to treat all scar types at once, or from mistaking social media “after” lighting for a medical outcome. Real scar revision is slower, steadier, and more believable than that.
Frequently Asked Questions About Acne Scar Removal
What actually gets rid of acne scars?
Nothing erases them entirely, but structural treatments change them most: subcision releases tethered rolling scars, fractional CO2 and RF microneedling rebuild collagen under depressed scars, and targeted techniques such as CROSS-style TCA application treat ice pick scars. Contrast that with marks — flat brown or red discolouration responds to topical brightening and time, no device required.
Is retinol effective for acne scars?
Retinol and prescription retinoids help two things: preventing new scars by keeping acne controlled, and modestly improving shallow textural irregularity through cell turnover and collagen support. Retinoids play a supportive role in managing mild texture, but they are not a substitute for procedural treatment once a deep collagen deficit exists. Patients who expect retinol alone to lift a boxcar scar are often disappointed; those who use retinoids to keep skin clear while undergoing scar revision tend to get better final results.
What is the best acne scar treatment in the UK?
There is no single answer, which is why the comparison matrix above exists. For deep atrophic scarring in lighter skin, fractional CO2 has the strongest evidence; for mixed scarring or darker skin tones, RF microneedling and staged combination plans usually deliver better risk-adjusted results.
Can laser treatment fix acne-related pigmentation?
Yes — Q-switched platforms such as our Nanosure pigmentation removal, from £95 per session, are designed for pigment rather than texture. The key is diagnosis first: pigment-only concerns don't need resurfacing at all.
How much does acne scarring laser treatment cost privately?
Most UK clinics charge £600–£1,500 per fractional CO2 session as a market range, with lighter options such as picosecond and RF microneedling in the £300–£700 band. Our own CO2 laser scar removal entry price starts from £250 per session for a specific offering. Always check what the quoted price includes — patch testing is offered with the free consultation.
Your Personalised Acne Scar Plan at 3D Aesthetics
Many patients reach this stage feeling stuck. They have read about lasers, microneedling, peels and fillers, but they still do not know what is appropriate for their own skin, or what is safe if they are prone to pigmentation.
That is the point where a proper in-person assessment becomes more useful than another treatment list. Finding the right acne scarring removal approach means selecting a plan that suits your scar pattern, skin behaviour, recovery tolerance, and goals.

What happens in a proper consultation
A good consultation should separate what is scarring from what is lingering pigmentation or redness. It should also identify whether you are dealing with rolling, boxcar, ice pick, or mixed scars, because those patterns rarely respond equally well to one treatment.
In clinic, assessing skin tone, sensitivity, previous reactions, active breakouts, and how your skin usually heals is essential. This matters even more in darker skin, where the wrong settings or an overly aggressive plan can leave you with pigment changes that last longer than the original blemishes. Safety is part of the result.
The treatment plan may include fractional CO2 resurfacing, 3D Dermaforce microneedling, or a staged combination chosen according to what your skin can tolerate. Stronger treatment can produce more visible change, but it usually comes with more downtime and a narrower margin for error. Gradual treatment is often safer for reactive skin and can still give meaningful improvement over time.
Why an individual plan works better than a fixed package
Fixed packages often fail to address individual patient needs. One patient may need more focus on texture and depth. Another may be more concerned by discolouration, visible pores, or scars that catch side light. Those are different complaints, and they should not be pushed into the same sequence of treatments.
A well-designed plan should answer a few practical questions:
- Which scar type is most dominant
- Which treatment is most likely to improve that specific texture issue
- Whether more than one modality is likely to be needed
- How much downtime fits your work, family life, and tolerance
- What level of improvement is realistic for your skin
That last point matters. In practice, the best plan is not always the most aggressive one. It is the one that gives worthwhile improvement with a risk profile you are comfortable accepting.
If you are ready for expert guidance, we invite you to book a free, no-obligation consultation with 3D Aesthetics Leamington Spa — patch testing is offered with the free consultation, and you will receive clear advice, realistic treatment options, and a plan designed specifically for your scar type, skin tone, and goals.
← Back to Home